Microsoft powerpoint - farraye & cross-case breakout-infections-print.pptx

Prevention and Treatment of

Opportunistic Infections in IBD
• 38 year old female pediatric nurse with 7 year
Patients: Case Studies
history of pan colitis doing well on
mesalamine
Francis A. Farraye MD, MSc
• In remission for 5 years
Clinical Director, Section of Gastroenterology
• Recent fl
are treated with
ith steroid
(20mg/d )
with transient improvement
Boston Medical Center
• Worsening symptoms so admitted to her local
Professor of Medicine
community hospital
Boston University School of Medicine
• C. diff negative
• Started on Solumedrol 20mg q 6h, increased
to 50mg q 6h on day 3
Background
• Global increase in the incidence of IBD
• Over next week, worsening symptoms with
• More patients on combination therapy:
decreasing HCT, albumin and increasing
steroids, anti-metabolites and biologic agents
bloody stools
• Immune system suppression predisposes to
• Infliximab added 5mg/kg on day 5
opportunistic infections
• Developed fever and d
yspnea on day 11
• CXR-infiltrates and hypoxia requiring
• Increasing reports of Pneumocystis Jiroveci
intubation
Pneumonia (PJP), formerly pneumocystis
• Diagnosed with Pneumocystis Jiroveci
carinii (PCP) in IBD patients
Pneumonia (PJP), formerly pneumocystis
• No evidence-based guidelines for
carinii (PCP)
prophylaxis
• Treated with Bactrim later changed to
Cosnes J, Gower-Rousseau C, Seksik P, Cortot A. Epidemiology and natural history of inflammatory
bowel diseases. Gastroenterology. 2011 May;140(6):1785-94. Poppers DM, Scherl EJ. Prophylaxis against

Atovaquone
Pneumocystis pneumonia in patients with inflammatory bowel disease: toward a standard of care.
Inflamm Bowel Dis. 2008;14:106-13.

Pneumocystis Jiroveci Pneumonia
Epidemiology of PJP in IBD Patients
• Ubiquitous unicellular fungus
• Case control study using administrative data from
• Develops in patients with defects in T-
IMS Health Inc, LifeLink™ Health Plan Claims
lymphocyte immunity
Database
• 108,604 patients with IBD matched to four non-IBD patients
• Exact incidence in IBD is unknown
• IBD patients had a 3.48-fold increased risk of PJP when
• Higher mortality in non-HIV patients
compared to non-IBD patients
• Absolute risk with biologic agents is debatable
• Incidence rate ratio, 4.49 (95% CI, 2.14-9.75) in CD
patients compared to non-IBD patients
• Risk increases with number of immune
modulating agents
• Incidence rate ratio, 2.40 (95% CI, 1.11-5.10) in UC
patients compared to non-IBD patients
• Passive FDA reporting system identified 84 PJP
• Incidence rate: 32/100,000 person-years vs.
cases between 1998-2003, 16 cases in IBD
4/100,000 person-years in non-IBD
patients
Kaur N, Mahl TC. Pneumocystis jiroveci (carinii) pneumonia after infliximab therapy: a review of 84 cases. Dig
Long MD, Farraye FA, Okafor PN, et al. Increased risk of PJP among patients with IBD. Inflamm Bowel Dis.
Dis Sci. 2007 Jun;52(6):1481-4.
2012, in-press.
Risk Factors for PJP in IBD
Recognizing PJP
• High degree of suspicion
• High dose corticosteroid use
• Triad of fever, hypoxia, cough
• Triple immunosuppressive therapy (steroids, anti-
metabolites, anti-TNF agents)
• Chest x-ray may show diffuse or no infiltrates
• Immunosuppresion with cyclosporine
• Slow progression in HIV, more rapid in non-HIV
cohorts culminating in respiratory failure with 30-
y phopenia (lym
y phocyte count
<600, CD4+ <300)
50% mortality
• Low TPMT levels
• Histopathological staining of sputum samples
• Advanced age
• PCR of sputum samples may be more sensitive
• Comorbidities, especially COPD
• Feasibility of oral washes in combination with PCR
• Recent CMV infection
merits additional studies
• Beta-D-glucan and KL-6 may have less utility in non-
Okafor PN, Nunes DP, Farraye FA. Pneumocystis Jiroveci Pneumonia in inflammatory bowel disease: When
should prophylaxis be considered? Inflamm Bowel Dis. 2012, in press.

HIV PJP due to smaller disease burden
Thomas CF, Limper AH. Pneumocystis pneumonia. N Engl J Med. Jun 10 2004;350(24):2487-2498. Catherinot E,
Lanternier F, Bougnoux ME, et al. Pneumocystis jirovecii Pneumonia. Infect Dis Clin North Am. 2010
Mar;24(1):107-38.
.

PJP Prophylaxis
PJP Prophylaxis
• Primary PJP prophylaxis is cost effective in
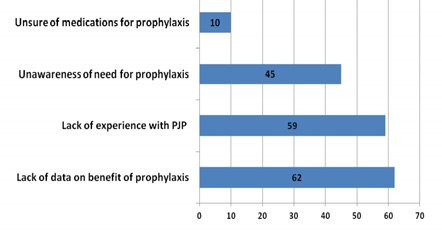
• Most cited reason for lack of prescribing prophylaxis
Wegener's granulomatosis when annual
was the lack of data or evidence-based guidelines to
direct practice
incidence is as low as 0.2%
• In an internet survey of US gastroenterology
iders, onl
prescribe PJP
prophylaxis
• Prior experience with PJP and practice in an
academic medical center were associated
with PJP prophylaxis
Okafor P, Wasan, SK, Farraye FA, Pneumocystis Jiroveci pneumonia in inflammatory bowel disease patients: A survey of
prophylaxis patterns among gastroenterology providers. Inflamm Bowel Dis 2012, in press.

Okafor P, Wasan, SK, Farraye FA, Pneumocystis Jiroveci pneumonia in inflammatory bowel disease patients: A survey
of prophylaxis patterns among gastroenterology providers. Inflamm Bowel Dis 2012, in press.

ECCO Guidelines
PJP Prophylaxis and Treatment
• ECCO guidelines (2009) based on expert
• Trimethoprim-sulfamethoxazole (Bactrim) most
commonly used because of cost, efficacy and side
– No vaccines for PJP
effect profile
– Recommend monitoring of cell counts
• Other options include dapsone, atovaquone,
pentamidine
– Primary prophylaxis with Bactrim for patients on
triple therapy
including
including biologic
• Treatment may
be i npatient
inpatient o
or outpatient
epending
depending
calcineurin inhibitors
on severity
– No consensus for dual therapy
• Corticosteroids indicated if PaO2 <70 mmhg, A-a
gradient >35mmhg
– Prophylaxis for steroid monotherapy debatable
• Involve infectious disease specialist early
• No guidelines for primary PJP prophylaxis
by US GI societies
Okafor PN, Nunes DP, Farraye FA. Pneumocystis Jiroveci Pneumonia in inflammatory bowel disease: When should
prophylaxis be considered? Inflamm Bowel Dis. 2012, in press.

Rahier, JF, Ben-Horin S, Chowers Y, et al., European evidence-based Consensus on the prevention, diagnosis
and management of opportunistic infections in inflammatory bowel disease. J Crohns Colitis, 2009. 3(2): 47-
91. Viget N, Vernier-Massouille G, Salmon-Ceron D, et al. Opportunistic infections in patients with
inflammatory bowel disease: prevention and diagnosis. Gut. Apr 2008;57(4):549-558.

Conclusions (1)
Conclusions (2)
• PJP in IBD patients is a growing concern
• Bactrim prophylaxis for patients on triple
• Fever is the principal and often the only initial
therapy as recommended by ECCO
manifestation of a serious infection
• Consider regular monitoring of lymphocyte
• Low incidence rates preclude feasibility of
counts for patients on dual agent or high
dose steroid monotherapy
• More case-control studies are needed
• Consider prophylaxis in high risk patients on
• Predictive models to identify patients at
triple immunosuppression OR monitor total
highest risk of PJP will be useful
lymphocyte and/or CD4+ counts closely
• A case-by-case approach to identify at-risk
• Early recognition and treatment is essential
groups that may benefit from prophylaxis is
recommended
Vesicular Rash in a CD Patient on
Herpes Zoster Epidemiology
• 55 year old female calls complaining of a rash
• At least 1 million people a year in the United
on her neck that began 24 hours earlier
States get shingles
• She thinks it is shingles because her father had
• Rash usually lasts from 2 to 4 weeks
similar rash several years ago
• Main symptom is pain, which can be quite
• Diagnosed with Crohn's Disease 12 years ago
• Limited ileocecal resection 8 years ago
• Very rarely, shi
es nfecti
tion can lead t
pneumonia, hearing problems, blindness,
• On 6MP for 8 years with surveillance
encephalitis or death
colonoscopy showing few aphthous erosions
in the neoterminal ileum
• Approximately 20% of patients can develop
post-herpetic neuralgia
• Rash typical of shingles
http://www.cdc.gov/vaccines/vpd-vac/shingles/vacc-need-know.htm
Herpes Zoster in IBD Patients
• Retrospective cohort study/nested case-control
• In the cohort study, the incidence of zoster was
study using 1988-1997 data from the General
higher in patients with CD and UC compared with
Practice Research Database
controls
• 7823 CD and 11,930 UC patients were matched
– UC incidence rate ratio, 1.21; 95% CI, 1.05-1.40
on age, sex, and primary care practice to 79,563
– CD incidence rate ratio, 1.61; 95% CI, 1.35-1.92
randomly selected controls without CD or UC
• In the nested case-control study, corticosteroids
• In the nested case-control study, 185 CD
(adjusted odds ratio, 1.5; 95% CI, 1.1-2.2) or
patients with zoster and 266 UC patients with
azathioprine/6-mercaptopurine (adjusted odds
zoster were matched on sex and year of birth to
ratio, 3.1; 95% CI, 1.7-5.6) were both associated
1787 IBD patients without zoster
with zoster
• IBD patients, especially those on
immunosuppressive medications, are at higher
risk for herpes zoster compared with the general
Gupta G, Lautenbach E, Lewis JD. incidence and risk factors for herpes zoster among patients with inflammatory
population
bowel disease. Clin Gastroenterol Hepatol. 2006;4: 1483–1490.
Gupta G, Lautenbach E, Lewis JD. incidence and risk factors for herpes zoster among patients with inflammatory
bowel disease. Clin Gastroenterol Hepatol. 2006;4: 1483–1490.

VZV Exposure History and
Immunity
Immunity
• History of VZV-related illness was accessed by
• The calculated positive and negative predictive
epidemiological questionnaire, and serological
values for the reported history of VZV exposure
testing for VZV-IgG was performed
were 93% and 0%
• 121 IBD (86% CD, mean age 37 ± 12.8) patients
• Negative history of VZV exposure is a poor
were studied
predictor of seronegativity
• 87% of th
tients were
on mmunomodulator
• History-positive patients may still be seronegative
therapy (anti-TNFs- 71%)
and exposed to VZV infection
• Previous exposure to VZV was reported by 104
• Suggest serological testing of all IBD patients with
patients, and 97/104 (93%) were VZV-IgG
subsequent immunization of the seronegative
seropositive
patients before initiation of immunosuppressive
• Seventeen patients, all seropositive, reported
negative exposure history
Kopylov U, Levin A, Mendelson E, et al. Prior varicella zoster virus exposure in IBD patients treated by
anti-TNFs and other immunomodulators: implications for serological testing and vaccination guidelines.
Kopylov U, Levin A, Mendelson E, et al. Prior varicella zoster virus exposure in IBD patients treated by
Aliment Pharmacol Ther. 2012 Jul;36(2):145-50.
anti-TNFs and other immunomodulators: implications for serological testing and vaccination guidelines.
Aliment Pharmacol Ther. 2012 Jul;36(2):145-50.
VZV Vaccine
VZV Vaccine
• Herpes Zoster vaccine first licensed in 2006
• One-time vaccination
• Lyophilized preparation of a live, attenuated
• No maximum age for getting the shingles vaccine
strain of varicella zoster virus (VZV)
• Anyone 60 years of age or older should get the
• Herpes Zoster vaccine reduced the risk of
shingles vaccine, regardless of whether they recall
shingles by 51% and the risk of post-herpetic
having had chickenpox or not
neuralgia b
cans ages 0
40 and older
• CDC recommends Herpes Zoster vaccine for use
have had chickenpox, even if they don’t remember
in people 60 years old and older to prevent
having the disease
shingles
• Patients with previous episode of shingles can
• The CDC does not have a recommendation for
receive Herpes Zoster vaccine
routine use of shingles vaccine in persons 50-59
years old but the vaccine is approved by FDA for
people in this age group
http://www.cdc.gov/vaccines/vpd-vac/shingles/vacc-need-
know.htm
http://www.cdc.gov/vaccines/vpd-vac/shingles/vacc-need-
know.htm
Vaccinating IBD Patients on
Immunomodulators with Zoster Vaccine
In 2008, the CDC determined that patients receiving low
• Of the 21 patients enrolled thus far, 9 are on immunomodulator
dose immunomodulators are not sufficiently
immunosuppressed to create vaccine safety concerns
• None of the patients developed a varicella-like rash
and can receive VZV
Methotrexate (≤0.4mg/kg/week), azathioprine (≤
• None of the patients noted an increase in IBD activity after
3.0mg/kg/day), 6-mercaptopurine (≤1.5mg/kg/day)
administration of VZV
Study Design
• Patients on
immunosuppressiv
immunosuppressiv therapy
increase
On-going prospective open-label study
specific antibody levels compared to the response noted in the
immunocompetent group (p=0.13 vs p=0.01)
Subjects
Patients ages 50 and older with IBD
• Baseline antibody levels were not different between the two
Group A: Currently on low dose immunomodulator
therapy, age 64 (51-76)
• Although immunosuppressed patients were able to mount a
Group B: On 5-ASA therapy or no therapy, age 50
statistically significant cytokine response following vaccination it
was reduced compared to the immunocompetent group (p=0.04)
Wasan SK, Berg AM, Liang YM, Ganley-Leal L, Farraye FA. Immune response and safety of herpes zoster
vaccine in IBD patients on methotrexate and thiopurines. Am J Gastroenterol. 2012;107:S668
Vaccinating IBD Patients on
Conclusions: VZV in IBD Patients
Immunomodulators with Zoster Vaccine
• Immunocompetent patients with IBD who were
• Risk of VZV is increased in immunosuppressed
vaccinated with VZV were able to increase their
IBD patients
antibody response to the vaccine antigens
• Up to 50% of adults born in tropical areas of the
world have no history of primary infection
• Immunosuppressed patients with IBD who were
vaccinated with VZV had much lower antibody
• Number of reports of severe, disseminated, and
responses to
antigens
rarely fatal v
aricella
varicella infection i n
immunosuppressed IBD patients
• Additional studies are needed to determine the
clinical significance of this blunted response and
• The risk of VZV infection is increased with all
whether the immunological response is protective
immunosuppressants, but corticosteroids and
or requires an altered vaccination regimen
combination immunosuppression appear to be a
particular risk
Wasan SK, Berg AM, Liang YM, Ganley-Leal L, Farraye FA. Immune response and safety of herpes zoster
Cullen G, Baden RP, Cheifetz AS. Varicella zoster virus infection in inflammatory bowel disease. Inflamm
vaccine in IBD patients on methotrexate and thiopurines. Am J Gastroenterol. 2012;107:S668
Bowel Dis. 2012 Mar 20. doi: 10.1002/ibd.22950. [Epub ahead of print]
Conclusions: VZV in IBD Patients
Cases Followup
• Healthcare providers need to be aware of the
• 38 year old woman with PJP
various manifestations of primary and secondary
– Intubated in ICU for 4 weeks
VZV infection in immunosuppressed IBD patients
– Survived and sent to rehab
• Patients should be screened for VZV immunity and
– Steroids tapered, PJP prophylaxis continued with
vaccinated prior to commencing
atovaquone
immunosuppression
– Patient refused to take 6MP
– UC flared with steroid taper and underwent colectomy
• 55 year old woman with Zoster
– 6MP held and antiviral therapy (famciclovir) started
– Rash resolved after one week
– No post herpetic neuralgia
– Received Herpes Zoster vaccine
Cullen G, Baden RP, Cheifetz AS. Varicella zoster virus infection in inflammatory bowel disease. Inflamm
Bowel Dis. 2012 Mar 20. doi: 10.1002/ibd.22950. [Epub ahead of print]

Source: http://www.advancesinibd.com/assets/Slides/clinical/Farraye%20&%20Cross-case%20breakout-infections-print.pdf

Goloy 33 eye care vitalize (der ultimative frische-kick für makellose augenpartien)

GOLOY 33 Eye Care Vitalize (new youthfulness around your eyes and the mouth) Water (as dissolver); together with hygroscopic agents; renders the subcorneous of the skin smooth, lissome and flexible Based on coconut; basic element of al fats and oils; hydrophilic; wetting agent Ester of coconut; gives higher elasticity and smoothness Texture maker from plants; emulsifier for O/W compounds P

Microsoft word - er11-3064.doc

April 1, 2011 Ms. Kimberly D. Bose Secretary Federal Energy Regulatory Commission 888 First Street, N.E. Washington, DC 20426 Re: Trans-Allegheny Interstate Line Company; Docket No. ER11-3064-000 Dear Madam Secretary: Attached for electronic filing are Comments of Exelon Corporation. A. Karen Hill Attorney for Exelon Corporation UNITED STATES OF AMERICA BEFORE THE FEDERAL ENERGY REGU

© 2010-2017 Pdf Pills Composition